|
Reviewed by Gavin Moreland, MD
|
Updated Sep 15, 2026 · 10 min read
Leafwell’s licensed providers help patients with depression explore medical cannabis as a supervised, adjunct treatment option — online, same day, in most states.
- ✓Depression qualifies directly in Alabama and Puerto Rico — and Missouri covers debilitating psychiatric disorders
- ✓In most states, patients qualify via a co-occurring condition — PTSD, anxiety, chronic pain, or insomnia
- ✓Physician-supervised, lab-tested, state-regulated products

Depression qualifies directly in a few states — and the conditions that often accompany it qualify in many more. Get your recommendation today.
Key takeaways
- Depression is listed directly in Alabama and Puerto Rico; Missouri covers “debilitating psychiatric disorders” diagnosed by a state-licensed psychiatrist
- In roughly 15 states, a licensed provider may certify any condition they determine may benefit — including depression
- Everywhere else, the practical route is a co-occurring diagnosis: PTSD, anxiety (where listed), chronic pain, or insomnia
- THC dose matters — a low dose eased stress responses in a controlled trial, while higher doses increased negative mood
- CBD engages serotonin 5-HT1A receptors — the same signaling system targeted by many antidepressants — without intoxication

65%
of patients with depression reported improved quality of life

64%
reduction in anxiety symptoms reported by medical cannabis patients

35%
improvement in sleep quality among patients using medical cannabis
Understanding depression and its impact
Major depressive disorder is one of the most common mental health conditions in the United States — an estimated 21 million adults (8.3%) experienced at least one major depressive episode in the past year. [1] Depression goes beyond sadness: persistent low mood, loss of interest in activities, changes in sleep and appetite, fatigue, difficulty concentrating, and feelings of worthlessness can affect every part of daily life.
Depression rarely travels alone. It frequently co-occurs with anxiety, PTSD, chronic pain, and insomnia — a clinical reality that matters for medical cannabis eligibility, because in most states one of those co-occurring conditions is the qualifying route.
When depression continues despite treatment
First-line treatments — SSRIs, SNRIs, and psychotherapy such as CBT — help many people, but a substantial share of patients do not reach remission with the first treatment they try. Side effects like emotional blunting, weight change, and sexual dysfunction lead others to discontinue. When depression persists despite conventional treatment, patients and providers may discuss additional approaches. Medical cannabis enters those conversations not as a replacement for antidepressants or therapy, but as a potential adjunct option within a supervised medical framework.
How cannabis may help depression
Cannabis interacts with the endocannabinoid system (ECS), which helps regulate mood, stress response, and reward circuitry. The two primary compounds behave differently:
- THC (Tetrahydrocannabinol): Effects on mood are dose-dependent. In a controlled trial, a low dose (7.5 mg) reduced the emotional response to a stress task, while a higher dose (12.5 mg) increased negative mood. [6] Naturalistic data show short-term reductions in self-reported negative affect, without evidence of a lasting antidepressant effect. [5]
- CBD (Cannabidiol): A non-intoxicating compound that engages serotonin 5-HT1A receptors — the same signaling system targeted by many antidepressants. Preclinical studies show antidepressant-like effects, though a systematic review found high-quality clinical trials in mood disorders are still lacking. [4]
Observational evidence is encouraging but not definitive. In the UK Medical Cannabis Registry, patients with depression reported that their PHQ-9 depression scores roughly halved at six months of treatment, [2] with improvements sustained at up to 24 months. [3] These are registry data, not randomized trials — and some research associates heavy, high-THC use with worse depression outcomes. Dose, formulation, and medical supervision matter more for depression than for almost any other condition.
CBD is metabolised by the cytochrome P450 enzyme system and can raise blood levels of some antidepressants, including certain SSRIs and tricyclics; combining cannabis with sedating medications can amplify drowsiness. Never stop or replace a prescribed antidepressant without your prescriber — abrupt discontinuation can cause withdrawal symptoms. High-THC products can worsen anxiety or low mood in some patients, and cannabis is not recommended for people with a history of psychosis. If you are having thoughts of self-harm, call or text 988 (Suicide & Crisis Lifeline). Always disclose all medications at your Leafwell appointment.
Depression may qualify you for a medical cannabis card.
See if you qualify in your state — most approvals completed same day.
- ✓Get approved in minutes
- ✓Same-day appointments available
- ✓Money back guarantee
Choosing cannabis products for depression
For depression more than most conditions, product selection is about restraint: cannabinoid ratio, dose, and timing matter more than strain names.
- High-CBD, low-THC tinctures and capsules: Non-intoxicating and daytime-appropriate; often the first suggestion for mood support.
- Balanced THC:CBD products: CBD may temper THC’s anxiety-provoking side effects; start low and titrate slowly.
- Low-dose THC edibles or tinctures: Precise dosing matters, because THC’s mood effects reverse at higher doses.
- What to avoid: High-THC concentrates and heavy daily use — patterns associated with worse mood outcomes in some studies.
Responses vary from person to person, which is why individualized medical guidance is recommended before starting cannabis for depression. For a closer look at specific cultivars patients discuss, see our guide to the best strains for depression.
Depression and medical marijuana eligibility by state
Depression qualifies for a medical marijuana card by name in only a few places — Alabama and Puerto Rico list it directly, and Missouri covers “debilitating psychiatric disorders” when diagnosed by a state-licensed psychiatrist. In roughly fifteen more states, a licensed provider may certify any condition they determine may benefit. Everywhere else, patients typically qualify through a co-occurring diagnosis such as PTSD, anxiety, chronic pain, or insomnia.
| State | Depression qualifying? | How to qualify |
|---|---|---|
| Alabama | Yes — listed directly | Depression is a named qualifying condition; documented failure of conventional treatment required (restricted product forms) |
| Alaska | No | Closed symptom list; no practical route for depression |
| Arizona | Not directly | Via PTSD or severe and chronic pain |
| Arkansas | Not directly | Via PTSD or intractable pain (unresponsive to treatment for more than 6 months) |
| California | Provider discretion | Broad catch-all — any condition for which cannabis provides relief; depression certifiable |
| Colorado | Not directly | Via PTSD, severe pain, or a condition for which a physician could prescribe an opioid |
| Connecticut | Not directly | Via PTSD or a listed pain condition; no practitioner catch-all |
| Delaware | Provider discretion | Catch-all — any condition a practitioner determines would provide therapeutic benefit |
| Florida | Provider discretion | Via the “same kind or class” clause — physician discretion with documentation; PTSD also listed |
| Georgia | Not directly | Via PTSD or intractable pain (closed list) |
| Guam | Not directly | Via PTSD or a qualifying debilitating condition |
| Hawaii | Provider discretion | Catch-all since Act 241 (2025) — provider may certify any diagnosed condition; PTSD also listed |
| Illinois | Not directly | Via PTSD, chronic pain, or the Opioid Alternative Program (21+) |
| Iowa | Not directly | Via PTSD or chronic pain (limited-THC program) |
| Kentucky | Not directly | Via PTSD or chronic, severe, intractable pain |
| Louisiana | Provider discretion | Catch-all — any condition a clinician considers debilitating; PTSD also listed |
| Maine | Provider discretion | No condition list; provider certifies likely therapeutic benefit |
| Maryland | Provider discretion | Catch-all — severe chronic condition where other treatments have been ineffective; chronic pain also listed |
| Massachusetts | Provider discretion | Catch-all — “other conditions as determined in writing” by the certifying clinician |
| Michigan | No — petition rejected | Review Panel declined depression in 2018; via PTSD, OCD, or chronic pain |
| Minnesota | Provider discretion | Catch-all — any condition the practitioner has authorized cannabis for; PTSD also listed |
| Mississippi | Not directly | Via PTSD or the chronic-pain symptom clause |
| Missouri | Yes — psychiatric category | “Debilitating psychiatric disorders” qualify when diagnosed by a state-licensed psychiatrist; physician catch-all also available |
| Montana | Not directly | Via PTSD or severe chronic pain (no catch-all or petition) |
| Nevada | Not directly | Via an anxiety disorder (listed with no severity qualifier) or severe/chronic pain |
| New Hampshire | Provider discretion (21+) | 21+ catch-all where benefits likely outweigh risks; generalized anxiety disorder and moderate-to-severe PTSD also stand-alone |
| New Jersey | Not directly | Via anxiety, PTSD, or chronic pain (closed list; bona fide provider relationship required) |
| New Mexico | Not directly | Via anxiety disorder, PTSD, or severe chronic pain (no write-in diagnoses) |
| New York | Provider discretion | No condition list; any condition the provider deems suitable |
| Northern Mariana Islands | Not directly | Via PTSD or a qualifying debilitating condition |
| Ohio | Not directly | Via PTSD or chronic, severe, or intractable pain (depression not named) |
| Oklahoma | Provider discretion | No condition list; physician judgment |
| Oregon | Not directly | Via PTSD or the severe-pain symptom route |
| Pennsylvania | Not directly | Via anxiety disorders, PTSD, or severe chronic/intractable pain |
| Puerto Rico | Yes — listed directly | Depression is a named condition under Regulation 9038; anxiety and insomnia are also listed |
| Rhode Island | Not directly | Via PTSD or severe debilitating chronic pain |
| South Dakota | Not directly | Via PTSD or severe debilitating pain |
| Texas | Not directly | Via PTSD or a chronic-pain condition for which a physician would otherwise prescribe an opioid (no catch-all) |
| US Virgin Islands | Not directly | Via PTSD or a qualifying debilitating condition |
| Utah | Not directly | Via PTSD (with concurrent mental-health treatment), persistent pain lasting longer than two weeks, or a Compassionate Use Board petition |
| Vermont | Not directly | Via PTSD (with ongoing counseling) or chronic pain; requires a 3-month provider relationship |
| Virginia | Provider discretion | No condition list; any condition the practitioner determines would benefit |
| Washington | No | Closed list (“limited to the following”); via PTSD or intractable pain where present |
| Washington D.C. | Provider discretion | No condition list; adults 21+ may self-certify |
| West Virginia | Not directly | Via PTSD or severe chronic or intractable pain |
Note: Qualifying conditions change; confirm current rules during your Leafwell evaluation. States without active medical programs (Idaho, Indiana, Kansas, North Carolina, South Carolina, Tennessee, Wisconsin, Wyoming; Nebraska’s program is still being implemented) are not listed.
How patients with depression access medical cannabis
- Medical evaluation — A licensed provider reviews your diagnosis, symptom history, and current medications — including any antidepressants — to determine if medical cannabis is appropriate.
- Certification if appropriate — If the provider determines cannabis may be beneficial, they issue certification under your state’s medical marijuana program — for depression where it qualifies, or for a co-occurring condition where it does not.
- State registration — Patients complete registration with their state’s health department to obtain the medical marijuana ID card.
- Access regulated products — Once approved, patients purchase lab-tested cannabis from licensed dispensaries with clearly labeled THC and CBD levels.
Depression may qualify you for a medical cannabis card.
Living with depression? Get your medical cannabis card online in minutes — with larger purchase limits and up to 40% in tax savings.
- ✓Get approved in minutes
- ✓Same-day appointments available
- ✓Money back guarantee
Medical cannabis helped Gavin find a brighter outlook.
After years of struggling with low mood and poor sleep, Gavin found that a supervised cannabis care plan helped him feel like himself again.

“It’s changed my whole outlook on life. I’m more positive now, and I’m getting much better sleep.”
Gavin, Leafwell patient since 2024 *name and photo changed for privacy
A cannabis care plan, tailored to your needs
We’ve made it simple to get personalized guidance from a cannabis-knowledgeable pharmacist — no medical card required.
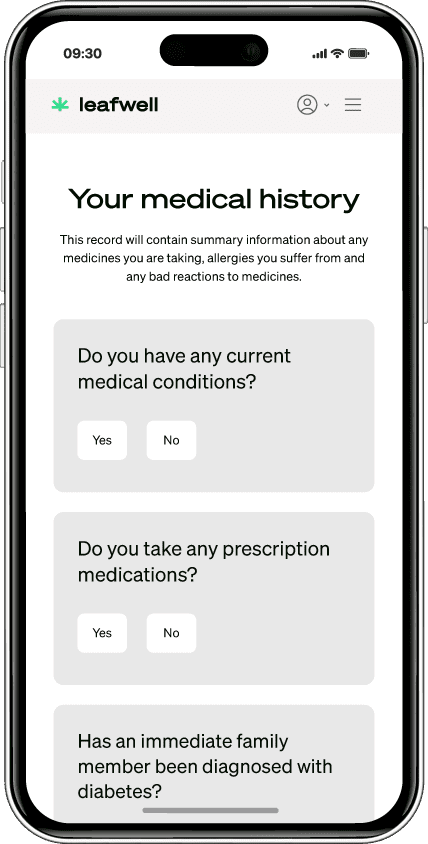
Complete a short questionnaire
Tell us about your medical history and mental health goals — takes under 5 minutes.

Meet with a Leafwell pharmacist online
A cannabis-knowledgeable pharmacist discusses your mood, sleep, and current medications in a confidential consultation.
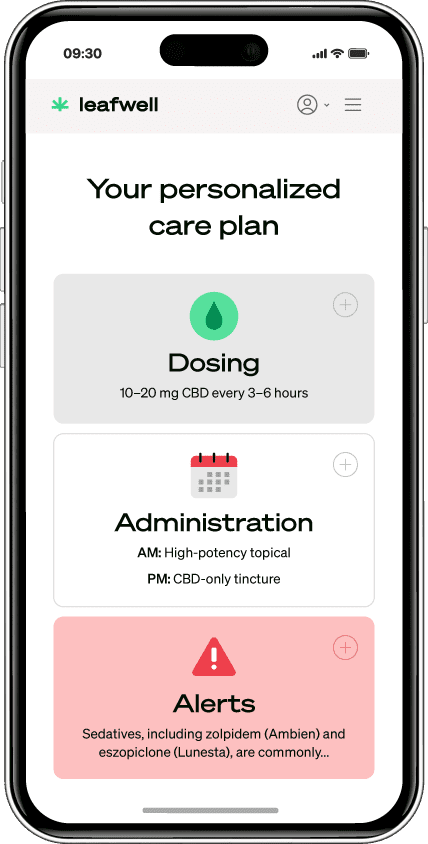
Get your product recommendations
Receive pharmacist-tailored product and dosing guidance suited to your mood and wellness goals.
Frequently asked questions
Can you get a medical cannabis card for depression?
It depends on your state. Alabama and Puerto Rico list depression directly, and Missouri covers debilitating psychiatric disorders diagnosed by a state-licensed psychiatrist. In roughly fifteen states, a licensed provider may certify any condition they determine may benefit. In most others, a co-occurring diagnosis — PTSD, anxiety (where listed), chronic pain, or insomnia — is the practical qualifying route. A Leafwell provider can tell you how depression is handled in your state.
Can cannabis make depression worse?
It can. THC’s effects on mood are dose-dependent: a low dose eased stress responses in a controlled trial, while a higher dose increased negative mood — and heavy, frequent, high-THC use has been associated with worse depression outcomes in some studies. Cannabis is also not recommended for people with a history of psychosis. This is why medical supervision, low starting doses, and regular check-ins matter.
Is CBD or THC better for depression?
They work differently. CBD is non-intoxicating and engages serotonin 5-HT1A receptors — the same signaling system targeted by many antidepressants — though high-quality clinical trials in mood disorders are still lacking. THC may lift mood at low doses but can worsen it at higher doses. Many providers suggest starting with high-CBD, low-THC formulations for mood support.
Does cannabis interact with antidepressants?
It can. CBD is metabolised by the cytochrome P450 enzyme system and may raise blood levels of some antidepressants, including certain SSRIs and tricyclics, and combining cannabis with sedating medications can amplify drowsiness. Never stop or change a prescribed antidepressant without your prescriber. Disclose all medications at your Leafwell appointment.
Which states list depression as a qualifying condition?
Alabama names depression directly on its qualifying-conditions list, and Puerto Rico lists depression in its medical cannabis regulation. Missouri covers “debilitating psychiatric disorders” — which can include depression — when diagnosed by a state-licensed psychiatrist. No other state currently names depression outright.
Can I qualify through PTSD, anxiety, or chronic pain instead?
Yes — this is the most common route. PTSD and chronic or severe pain are each listed in more than 30 states, and anxiety disorders are listed in several, including Nevada, New Jersey, New Mexico, and Pennsylvania. If you live with depression alongside one of these diagnoses, that condition can qualify you even where depression alone would not.
Do I need to stop my antidepressant to use medical cannabis?
No — and you should not stop an antidepressant on your own. Medical cannabis is explored as an adjunct, not a replacement, and stopping antidepressants abruptly can cause discontinuation symptoms. Your Leafwell provider will review your medications and coordinate an approach that keeps your current treatment intact.
How do I get a medical card for depression online?
Select your state, complete a video evaluation with a licensed Leafwell physician, and if approved you receive your certification the same day. Most patients complete the process in under 30 minutes.
Take a gentler, more natural path to a brighter outlook
Begin your journey now — schedule a physician consultation today and get approved in minutes.
References
- National Institute of Mental Health (2023). Major Depression: Statistics. U.S. Department of Health and Human Services.
- Rifkin-Zybutz R, et al. (2023). Clinical outcome data of patients with depression prescribed cannabis-based medicinal products: analysis from the UK Medical Cannabis Registry. Expert Review of Neurotherapeutics. doi:10.1080/14737175.2022.2161894
- UK Medical Cannabis Registry (2026). Clinical outcomes of patients with depression treated with cannabis-based medicinal products at up to 24 months. Journal of Affective Disorders. PMID: 41506388
- Pinto JV, et al. (2020). Cannabidiol as a Treatment for Mood Disorders: A Systematic Review. Canadian Journal of Psychiatry, 65(4), 213–227. doi:10.1177/0706743719895195
- Cuttler C, et al. (2018). A naturalistic examination of the perceived effects of cannabis on negative affect. Journal of Affective Disorders, 235, 198–205. doi:10.1016/j.jad.2018.04.054
- Childs E, et al. (2017). Dose-related effects of delta-9-THC on emotional responses to acute psychosocial stress. Drug and Alcohol Dependence, 177, 136–144. doi:10.1016/j.drugalcdep.2017.03.030
- Ergisi M, et al. (2022). UK Medical Cannabis Registry: an analysis of clinical outcomes of medicinal cannabis therapy for generalized anxiety disorder. Expert Review of Clinical Pharmacology, 15(4), 487–495.